

If your treatment is “okay” but not great, that’s worth a conversation. Here’s what to watch for and what to say to your doctor.
“Psoriatic disease” includes both psoriasis (PsO) and psoriatic arthritis (PsA). Many people living with one or both stay on the same treatment for years, even when it’s only partly working. Some are still using creams that don’t keep up with their symptoms. Others started a pill or shot that helped at first but no longer does as much.
You don’t have to settle. Experts now agree on clear signs that someone may need a stronger treatment. Older approaches to rating psoriasis as mild, moderate, or severe often didn’t fully account for psoriasis in hard-to-treat areas or for a person’s treatment history, which could sometimes result in undertreatment. And there are now many creams, pills, and biologic medicines to choose from.
“I decided to get another rheumatologist, and the medication that I’m on now, amazingly, started working the same day like I felt a difference. I could walk again. I could take care of myself again. I was able to be independent. You don’t need to check every box. Even one of these is a good reason to start the conversation.” — Minionette, 56, living with psoriasis and psoriatic arthritis
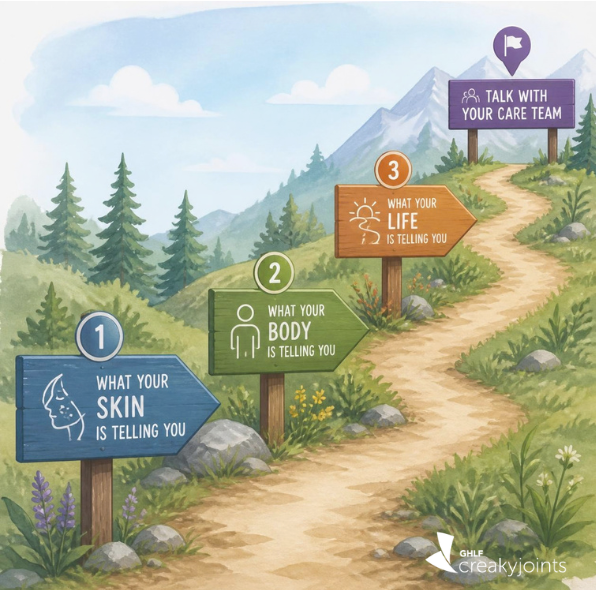
What Your Skin Is Telling You
Your skin isn’t clear, or almost clear, after 3 months. Experts have set a clear goal for psoriasis treatment. After three months on a new treatment, the target is for psoriasis to cover 1 percent or less of your body. Your whole hand, including the palm, fingers, and thumb, is about 1 percent of your body.[3] If you haven’t reached an acceptable level of improvement by 3 months, or the target by 6 months, it’s time to talk with your health care provider about other options.
Your creams aren’t doing the job. Creams and ointments are often the first treatment people try, but they don’t work for everyone. An international group of psoriasis experts defines topical treatment as “not working” when someone can’t get clear or nearly clear skin after two 4-week courses in a row. People whose psoriasis isn’t controlled by creams alone may be candidates for treatment that works throughout the body, even if only a small area is affected.
Psoriasis is on your scalp, face, hands, feet, nails, or genitals. Where your psoriasis appears matters as much as how much of your skin it covers. Experts call these high-impact sites: the face, palms, soles, genitals, scalp, and nails. Psoriasis in these areas can be painful, hard to treat with creams, and hard to hide. It can also be uncomfortable to bring up, but your care team has heard it all before.
“The skin rashes were unbearable,” Minionette shares. “I had several. They would be in the creases of my arms, on my neck and sometimes my entire scalp, and that is really hard to deal with, because you don’t want to comb your hair, you don’t want to wash your hair, you just don’t want to do anything with your head at all, because it is very, very painful and very irritating.”
It’s spreading or flaring more often. New spots, or flares that keep coming back, may mean your treatment isn’t strong enough. Take photos over time so you can show your care team what’s changing between visits.
What Your Body Is Telling You
Your joints hurt, feel stiff, or are swollen. About one in three people with psoriasis may develop psoriatic arthritis, which can cause joint swelling, stiffness, and pain. Watch for morning stiffness, swollen fingers or toes, heel pain, or back pain. Creams can’t reach your joints, so joint symptoms are an important reason to talk about your treatment.
“I started to have swelling back pain, like, anytime I sat in a chair would hurt really bad…had swelling fingers and inability to have full mobility of being able to bend my fingers.” –Stephen, 36, living with psoriasis and psoriatic arthritis
Your treatment doesn’t seem to work as well anymore. If you’re not feeling as well as you once did, it might be time for a change in treatment or even an adjustment to your medication dosage or schedule. Talk with your doctor about your options.
What Your Life Is Telling You
It’s getting in the way of daily life. Maybe you avoid certain clothes, skip the gym, dread haircuts, or have trouble sleeping because of itching or pain. These everyday effects count. You don’t need to wait until things feel “bad enough.”
It’s affecting how you feel emotionally. Living with a visible, chronic condition can take a toll. Studies show people with psoriasis are at least one and a half times more likely to experience depression. Tell your care team how you’re feeling. It’s part of your health, and they can help.
Your treatment doesn’t fit your life. Some treatments take a lot of time or effort, like applying several creams twice a day. Others may cause side effects that bother you. If your treatment doesn’t fit your routine, it’s fair to ask what else is out there, including pills, shots, and other options.
“Through talking with my rheumatologist, my dermatologist, and CreakyJoints, it has helped me see that my situation can be so different and a much easier journey than what I had seen before. And so I’m now at a place where it’s manageable, and I think I feel better, more content or at peace with it now than obviously, than when I first was diagnosed.” – Ashley, 42, living with psoriasis and psoriatic arthritis
You feel like it “isn’t that bad,” but it’s still bothering you. Your own sense of how you’re doing matters. Experts say a patient’s self-assessment should strongly influence treatment decisions, especially when they feel their disease is moderate or severe.[4] If it bothers you, it’s worth talking about.
How To Talk with Your Care Team About A Change
Your care team may include a dermatologist, a rheumatologist, a nurse practitioner (NP), or a physician assistant (PA). NPs and PAs are often the people you see most. They can prescribe medications and other treatments (depending on state law) and teach patients and families about managing their condition and treatment.[7] You can bring up a treatment change with any member of your team.
Before your visit:
- Track your symptoms. Take photos of your skin and note joint pain, sleep, and flares.
- Think about what matters most to you, such as fast results, convenience, pills vs. shots, or fewer side effects.
- Make a list of questions. Prepare for the appointment by listing your concerns, trends in how you’ve been doing, and questions you have.
During your visit, you might ask:
- “Is my psoriasis or PsA where it should be by now?”
- “Am I a candidate for a different kind of treatment?”
- “What are my options, and how do they compare?”
- “How will we know if the new treatment is working?”
Made with support from Bristol Myers Squibb
Dowlatshahi EA, et al. The prevalence and odds of depressive symptoms and clinical depression in psoriasis patients: a systematic review and meta-analysis. J Invest Dermatol. 2014;134:1542-1551. doi:10.1038/jid.2013.508
MedCentral. Psoriasis, Psoriatic Arthritis, and Effective Treat-to-Target. February 2024 (citing National Psoriasis Foundation). (Consider replacing with the NPF primary source.)
National Psoriasis Foundation. Treat to Target. See also: Armstrong AW, et al. From the Medical Board of the National Psoriasis Foundation: Treatment targets for plaque psoriasis. J Am Acad Dermatol. 2017;76(2):290-298. (Verify page numbers.)
Strober B, et al. Recategorization of psoriasis severity: Delphi consensus from the International Psoriasis Council. J Am Acad Dermatol. 2020;82(1):117-122. doi:10.1016/j.jaad.2019.08.026
Strober BE, et al. Establishing consensus on defining failure of topical therapy in psoriasis: Recommendations from the International Psoriasis Council. J Am Acad Dermatol. 2026;94(1):372-375. doi:10.1016/j.jaad.2025.08.116



